Evidence-based response
What Is the Best Gut Microbiome? Evidence-Based Answer Without the Hype
There is no single best gut microbiome score. A healthy microbiome is context-dependent, and consumer stool tests cannot diagnose overall gut health on their own.
By Sandra McKenzy, Pharmacist · 2026-05-27
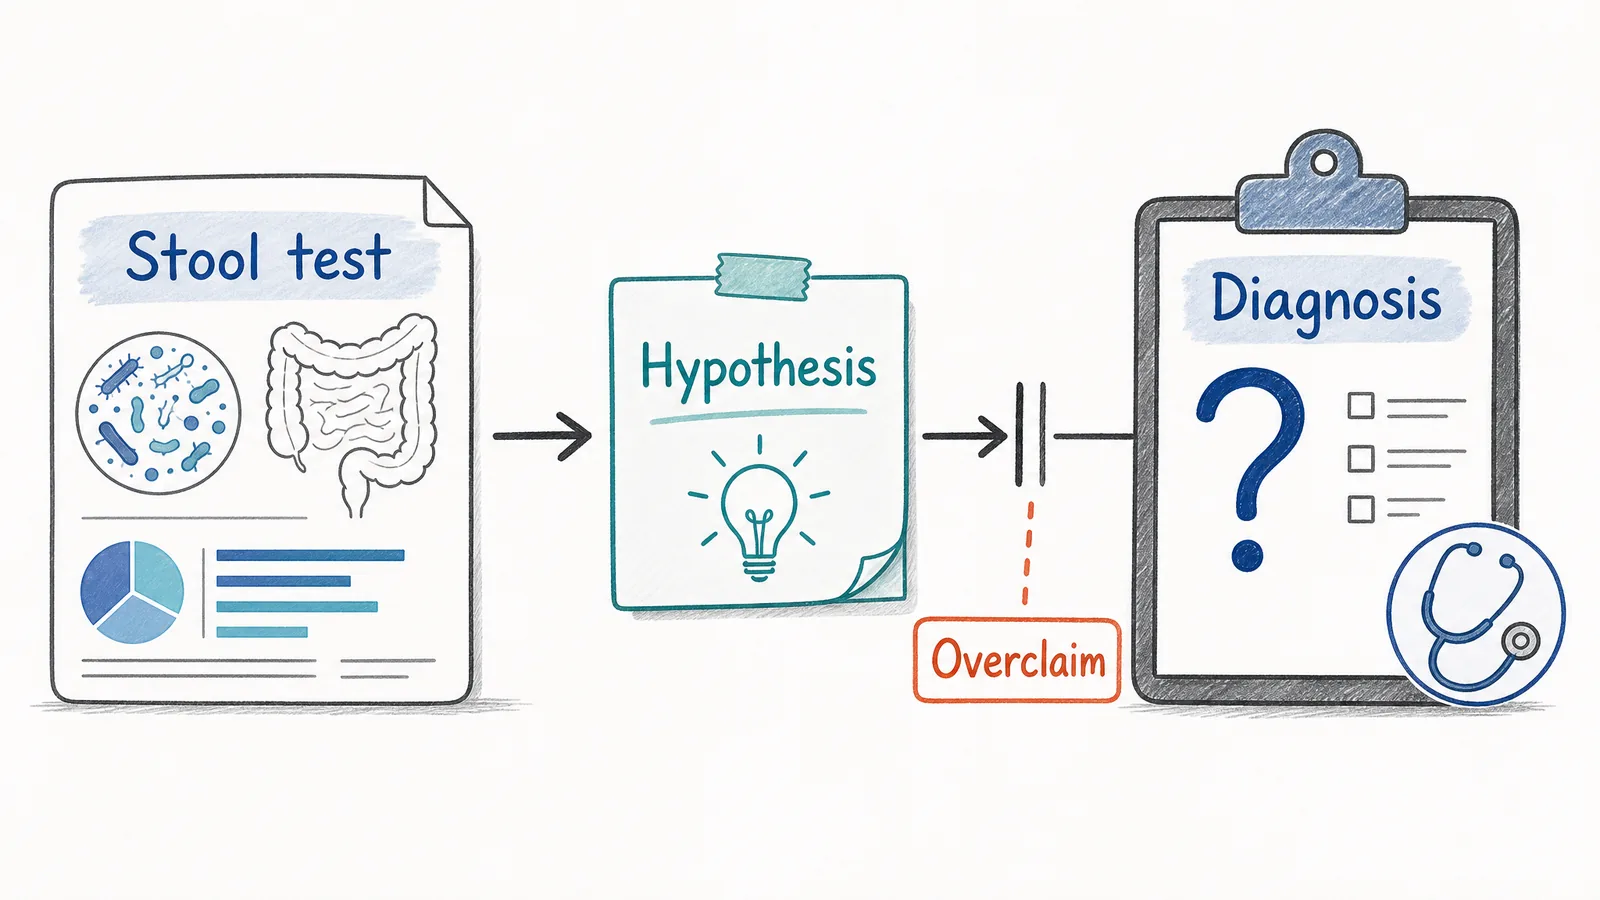
Short answer: The best gut microbiome is not a universal list of good bacteria or one diversity score. It is a resilient, well-functioning ecosystem that supports digestion, barrier function, immune tolerance, and metabolic signaling in the context of a person’s symptoms, diet, medications, and health history. A stool test can describe patterns, but it cannot certify that your microbiome is optimal.
What does “best gut microbiome” actually mean?
Scientifically, this question is harder than most wellness pages make it sound. Healthy gut ecosystems vary across geography, diet, age, stool consistency, medication exposure, and sequencing method. Two healthy people can have different microbial profiles, and the same person can shift over time.
That is why a good answer starts with function, not a leaderboard. A clinically reassuring gut pattern is usually one that helps ferment dietary fibers, produces short-chain fatty acids, supports the intestinal barrier, resists pathogen overgrowth, and coexists with normal digestion. But those features are inferred from patterns. They are not the same as a diagnosis.
Is microbiome diversity always the goal?
Diversity is often useful as a rough ecological marker. Low diversity can be seen after antibiotics, with highly restricted diets, or in some disease states. But “more diversity” is not automatically better for every person. A diverse stool sample can still include unwanted organisms, and a lower-diversity pattern may reflect recent diet, diarrhea, bowel prep, medication, or sampling variation.
The stronger practical claim is modest: varied, minimally processed plant foods tend to provide more fermentable substrates for gut microbes. That can support short-chain fatty acid production and broader microbial activity. It does not mean every person should chase a perfect diversity number.
Can a stool test tell you whether your gut microbiome is the best?
Consumer microbiome tests can identify organisms detected in a stool sample and sometimes report broad patterns such as low diversity, low representation of fiber-associated taxa, or possible methane-associated organisms. That information may generate useful hypotheses.
It should not be treated as a stand-alone health verdict. Current microbiome testing is not a substitute for a clinical history, physical examination, blood tests, stool inflammation markers, breath testing, endoscopy, imaging, or other validated tools when symptoms are significant. InnerBuddies and similar services may provide educational reports, but the clinical bridge from a stool profile to precise personal treatment remains limited.
What is actually supported?
- A single universal “best microbiome” has not been clinically defined.
- Healthy microbiomes vary by person, region, diet, age, medication exposure, and methods.
- Dietary pattern, especially fiber variety, can shift microbial composition and fermentation.
- Diversity is a useful ecological clue, not a diagnosis or wellness score by itself.
- Consumer stool tests can generate hypotheses, but they do not replace validated clinical evaluation.
Which gut bacteria are usually discussed as beneficial?
Commonly discussed groups include Bifidobacterium, Lactobacillus, Faecalibacterium, Roseburia, Akkermansia, and other fiber-fermenting or mucus-associated organisms. These names matter in research, but context matters more than isolated presence or absence. A bacterium that is associated with health in one setting may not be a treatment target in another.
The most defensible everyday strategy is not to micromanage one species. It is to support the ecosystem with enough tolerated plant diversity, adequate protein and sleep, regular movement, and careful antibiotic use when medically appropriate.
When should gut symptoms be checked clinically?
Do not use a microbiome score to explain away red flags. Blood in stool, persistent diarrhea, night-time symptoms, unexplained weight loss, fever, anemia, severe abdominal pain, new symptoms after age 50, or a family history of colorectal cancer or inflammatory bowel disease deserve medical assessment.
Bottom line
The best gut microbiome is not a fixed bacterial shopping list. It is a context-dependent, resilient ecosystem that supports normal function. Testing can be informative, but it should be read as one clue, not as proof that your gut is healthy, damaged, or in need of a specific protocol.
Evidence notes
- ISAPP consensus panel (2026). The International Scientific Association for Probiotics and Prebiotics consensus statement on the definition and scope of gut health. Nature Reviews Gastroenterology & Hepatology. 10.1038/s41575-026-01176-x
- Joos et al. (2025). Examining the healthy human microbiome concept. Nature Reviews Microbiology. 10.1038/s41579-024-01107-0
- He et al. (2018). Regional variation limits applications of healthy gut microbiome reference ranges and disease models. Nature Medicine. 10.1038/s41591-018-0164-x
- Quigley (2017). Gut microbiome as a clinical tool in gastrointestinal disease management: are we there yet? Nature Reviews Gastroenterology & Hepatology. 10.1038/nrgastro.2017.29
- David et al. (2014). Diet rapidly and reproducibly alters the human gut microbiome. Nature. 10.1038/nature12820
- Sonnenburg and Sonnenburg (2019). The ancestral and industrialized gut microbiota and implications for human health. Nature Reviews Microbiology. 10.1038/s41579-019-0191-8
This article is educational and does not diagnose, treat, or replace care from a qualified clinician.