Evidence-based response
7 Key Gut Bacteria Linked to Better Health: Benefits, Limits, and Red Flags
Several gut bacteria are linked to useful functions such as butyrate production and mucus ecology, but no seven-microbe checklist proves better health.
By Sandra McKenzy, Pharmacist · 2026-05-27
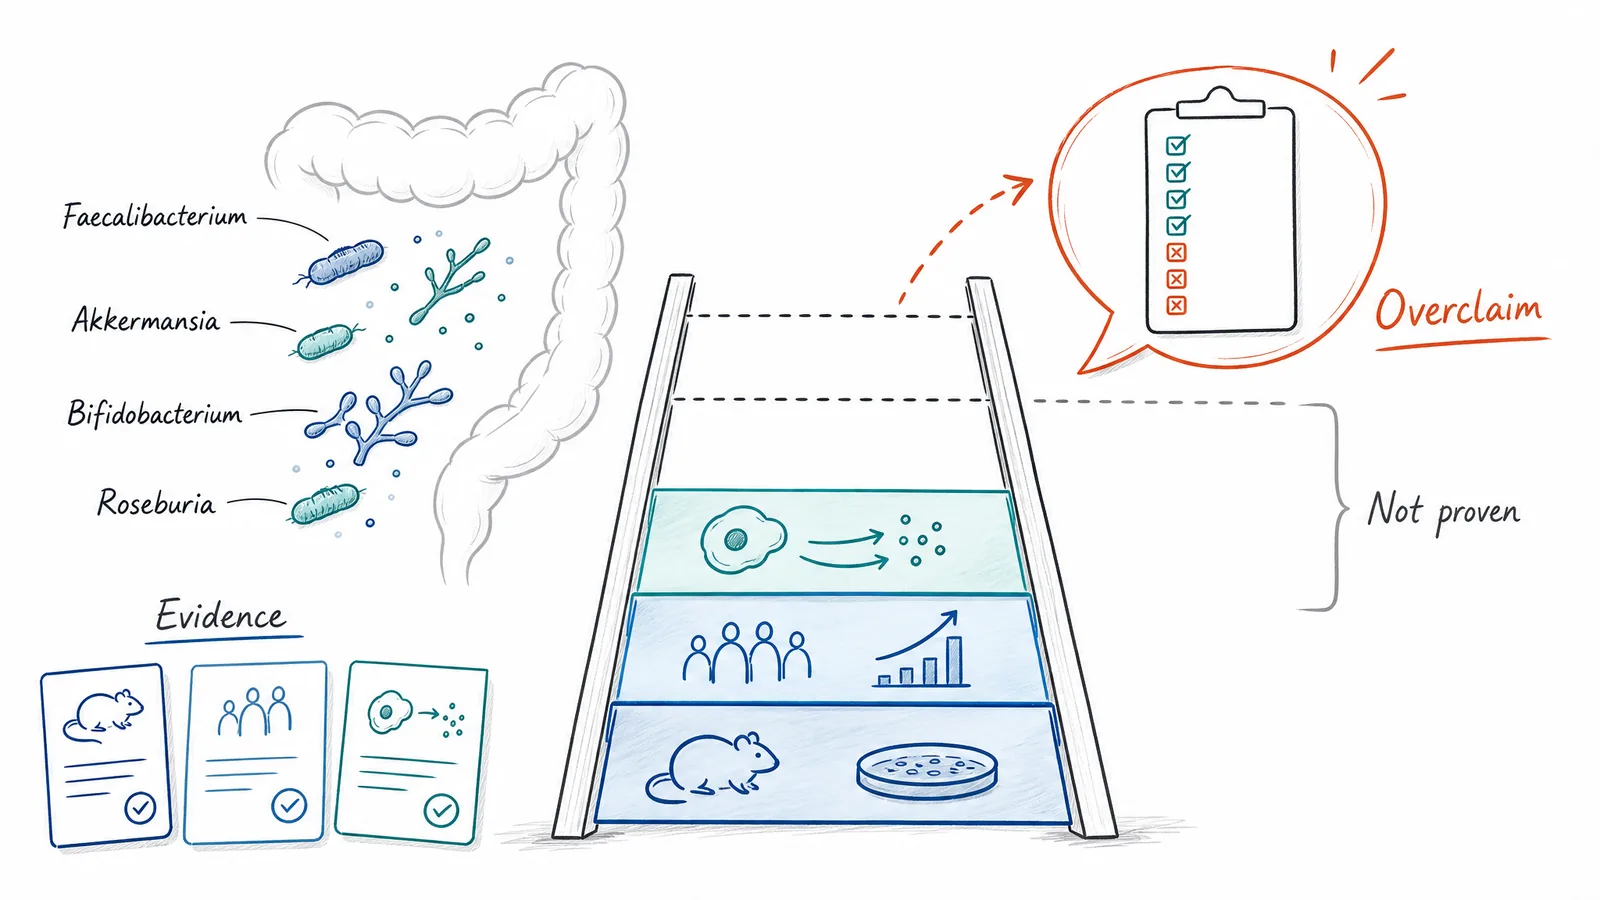
Short answer: Some named gut bacteria, including Faecalibacterium prausnitzii, Akkermansia muciniphila, Bifidobacterium, Roseburia, and selected Lactobacillus strains, are linked to functions that can support health. But no list of seven bacteria can diagnose your gut, guarantee better health, or tell you exactly what supplement or diet you need.
Are there really key gut bacteria linked to better health?
Yes, but the word linked matters. Microbiome studies consistently identify organisms associated with useful functions: fiber fermentation, short-chain fatty acid production, mucus-layer interactions, immune tolerance, bile-acid metabolism, and pathogen resistance. These functions are more clinically meaningful than simply naming bacteria as good or bad.
Faecalibacterium prausnitzii and Roseburia species are often discussed because they help produce butyrate, a short-chain fatty acid used by colon cells and involved in immune regulation. Akkermansia muciniphila is studied because it lives near the mucus layer and has been associated with metabolic health in some human and animal studies. Bifidobacterium and some Lactobacillus strains have probiotic evidence, but benefits depend on strain, dose, condition, and outcome.
Why a seven-bacteria checklist can mislead
The microbiome is an ecosystem, not a stamp collection. A bacterium that looks beneficial in one context may be neutral, absent, or difficult to interpret in another. Stool tests also measure relative abundance in a sample, not direct activity at the gut lining. Two healthy people can have different profiles, and the same person can shift with diet, medication, illness, travel, sleep, and stool consistency.
That is why a list of seven bacteria should not be used as a health score. Low Faecalibacterium can fit a low-fiber or inflammatory pattern, but it does not diagnose IBD. Higher Akkermansia can be interesting, but it does not prove metabolic protection. A probiotic genus name does not guarantee a clinical benefit unless the tested strain and condition match.
What claims go beyond the evidence?
Marketing often turns microbial associations into personal certainty: if you have less of one organism, you need a specific recommendation; if you increase another, your immunity, mood, metabolism, and digestion will improve. That is too strong. InnerBuddies and similar articles sometimes frame microbiome testing as a way to move beyond guesswork. Testing can reduce some uncertainty, but it can also create false precision when results are interpreted without symptoms, diet, medication history, and clinical context.
There is also no universal perfect microbiome. Researchers are still working out which microbial functions are robust enough for routine clinical decisions. For most people, the safest advice remains boring but evidence-aligned: diverse plant foods if tolerated, adequate fiber, sleep, physical activity, cautious antibiotic use, and medical assessment for persistent symptoms.
What is actually supported?
- Butyrate-producing bacteria such as Faecalibacterium and Roseburia are biologically important, but they are not stand-alone health tests.
- Akkermansia muciniphila has promising metabolic research, including early human work, but it is not a general wellness guarantee.
- Bifidobacterium and selected Lactobacillus strains can help specific outcomes, but probiotic effects are strain-specific.
- Microbial diversity is often useful as a broad ecology marker, not as a simple score to maximize in every person.
- Consumer microbiome tests should be treated as exploratory tools, not as diagnostic or prescribing systems.
Can you support beneficial gut bacteria?
The most defensible route is feeding microbial functions rather than chasing one organism. Gradually increasing tolerated plant diversity can support fermentation. Beans, lentils, oats, barley, vegetables, fruit, nuts, seeds, and resistant starches provide substrates for many fiber-adapted microbes. Fermented foods may suit some people, but they are not required and do not colonize everyone the same way.
If you have IBS, IBD, immune suppression, recent gut surgery, severe bloating, or strictures, do not abruptly increase fiber or probiotics. Personalization should start with clinical safety, not a leaderboard of bacteria.
When should symptoms be checked clinically?
Blood in stool, persistent diarrhea, unexplained weight loss, anemia, fever, night-time symptoms, severe abdominal pain, vomiting, or new symptoms after age 50 need medical evaluation. A missing or low bacteria result cannot rule out inflammatory bowel disease, celiac disease, infection, cancer, or medication-related injury.
Bottom line
Named gut bacteria can teach us a lot about microbiome function. They are useful signals in research and sometimes helpful context for nutrition decisions. But better health does not come from owning seven perfect microbes. It comes from matching microbial evidence with symptoms, diet, risk factors, and real clinical boundaries.
Evidence notes
- Sokol et al. (2008). Faecalibacterium prausnitzii is an anti-inflammatory commensal bacterium identified by gut microbiota analysis of Crohn disease patients. PNAS. 10.1073/pnas.0804812105
- Parada Venegas et al. (2019). Short chain fatty acids mediated gut epithelial and immune regulation. Frontiers in Immunology. 10.3389/fimmu.2019.00277
- Depommier et al. (2019). Supplementation with Akkermansia muciniphila in overweight and obese human volunteers. Nature Medicine. 10.1038/s41591-019-0495-2
- Rivière et al. (2016). Bifidobacteria and butyrate-producing colon bacteria: importance and strategies for their stimulation. Frontiers in Microbiology. 10.3389/fmicb.2016.00979
- La Rosa et al. (2019). The human gut Firmicute Roseburia intestinalis is a primary degrader of dietary beta-mannans. Nature Communications. 10.1038/s41467-019-08812-y
- Mizuno et al. (2017). Gut microbiome as a clinical tool in gastrointestinal disease management: are we there yet? Nature Reviews Gastroenterology & Hepatology. 10.1038/nrgastro.2017.29
This article is educational and does not diagnose, treat, or replace care from a qualified clinician.